NEW DELHI: When 33-year-old Khushboo Jaiswal walked into a private hospital in Burari, Central Delhi, she was expecting a calm and natural childbirth. After her water broke at home, she envisioned the standard progression of labor—gentle contractions, rhythmic breathing, and eventual delivery. Within hours, however, her expectations were entirely upended as she found herself wheeled into an operating table for a cesarean section.
"I was admitted to a hospital in Central Delhi when my water broke at home," Jaiswal recalled. "The doctor said my labor was taking too long, and a normal delivery will not be possible. And therefore, they will conduct a cesarean section. My family agreed. Before I knew it, I was in the operation theatre."
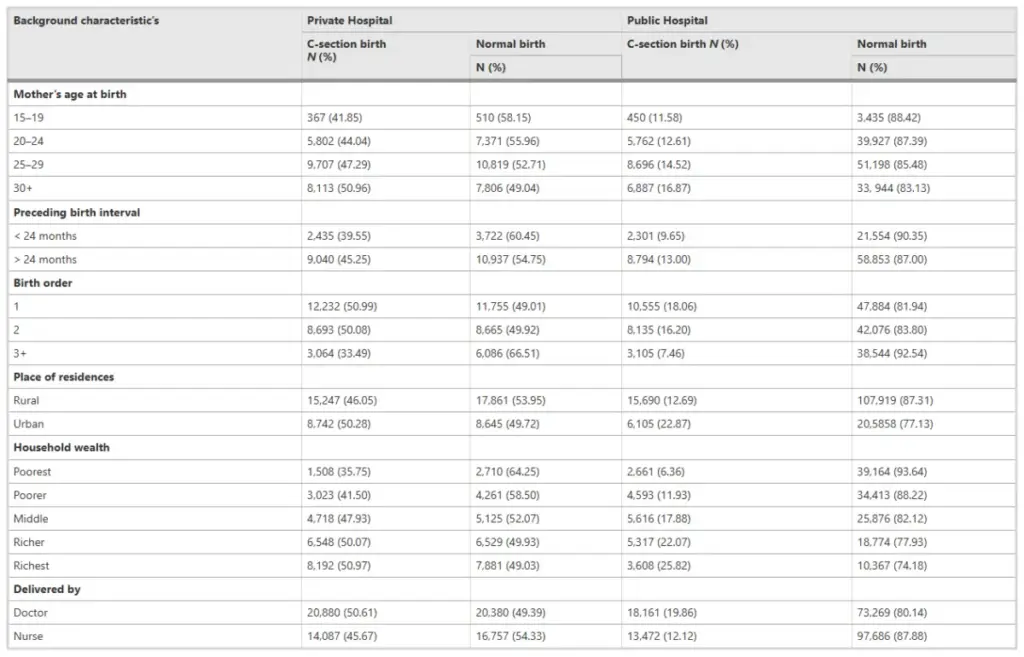
Jaiswal’s experience is no longer an isolated medical anomaly; it has become an increasingly common reality for women giving birth across India. According to the National Family Health Survey-5 (NFHS-5, 2019–21), nearly half of all births in private hospitals—approximately 48 percent—now happen through surgical intervention. In contrast, the rate stands at 14.3 percent in government-run hospitals. Even the public sector baseline sits above the World Health Organization’s (WHO) internationally recommended guideline, which states that the ideal population-level C-section rate should range between 10 and 15 percent.
The broader national data illustrates a steep upward trajectory. India’s overall caesarean birth rate has climbed to 22 percent, marking a significant jump from 17 percent just five years prior. While medical professionals universally agree that C-sections are vital, life-saving procedures in complicated or high-risk pregnancies, public health data demonstrates that a vast number of these surgeries are performed in the absence of absolute medical necessity.
For many women navigating maternity wards, the path to surgery is paved with subtle psychological pressure and fear. Jaiswal alleged that hospital staff often use alarming language to steer patients away from natural childbirth. "Nurses and doctors scare you in such a way that they would say something that would make you nervous and try to persuade you for a caesarean since it is a quick 50-60 minute process and is expensive; whereas, normal delivery takes 4-6 hours and is cheaper than caesarean," she alleged. "I feel they just want to make money and so they prefer only caesarean. Even one of my relatives went through the same situation."
This sentiment is echoed by public health advocates and senior medical practitioners who have watched the commercialization of maternity care accelerate over the past two decades. Dr. (Prof.) Sadhana Kala, a senior obstetrician and gynaecologist, points out that the structural economics of modern healthcare heavily favor surgical delivery.
"A large part of the problem stems from profit-driven incentives," Dr. Kala said. "Hospitals and doctors often earn more from surgical deliveries than from normal births. There is also a shift in medical culture. Many obstetricians today prefer surgical interventions over waiting through prolonged labor."

Childbirth across India has increasingly become a reflection of socioeconomic status, geography, and institutional access. The divide is stark across demographic lines. Data indicates that one in three urban births now happens through surgery, compared to roughly one in five births in rural areas. Furthermore, wealthier women are statistically five times more likely to undergo a C-section than women from lower-income households. Education also plays a pronounced role, with women possessing higher levels of formal schooling undergoing surgical births at noticeably higher rates than those with little or no education.
Geographically, the trends vary dramatically across states. Southern states record some of the highest reliance on surgical deliveries globally, led by Telangana at 60.7 percent and Tamil Nadu at 44.9 percent. Conversely, states like Bihar at 9.7 percent and Nagaland at 5.7 percent record some of the lowest rates in the country. In the national capital region of Delhi, the C-section rate stands at 23.6 percent.
The psychological toll on mothers caught in these clinical environments is profound. Shabnam, a 29-year-old mother from a Delhi suburb, shared a strikingly similar narrative. During her labor, she was informed that her baby’s heartbeat had begun to slow down, triggering an immediate shift in protocol.
"There was no real discussion, and I was really scared for my baby. I was taken straight into surgery," Shabnam said. Reflecting on the atmosphere in the delivery suite, she added, "I was pressurised by nurses or scared, I would say, it was a difficult situation for me. The doctor said my baby’s heartbeat was slowing. I did not know what questions to ask."
Addressing the broader systemic trends, Dr. Sunita Tandulwadkar, president of the Federation of Obstetric and Gynaecological Societies of India (FOGSI), emphasized that the rise in C-sections must be viewed through a multifaceted lens rather than a single causal factor.
"According to data from national health surveys and institutional reports, the overall rate has increased in both public and private sectors, although the proportion remains higher in private facilities," Dr. Tandulwadkar stated. "It is important to recognise that this trend is multifactorial and reflects evolving clinical, demographic and social realities rather than a single cause."
Among these contributing factors, Dr. Tandulwadkar noted the growing clinical reality of repeat surgeries. "A major contributing factor is the growing number of women with a previous caesarean delivery, who, for valid medical and safety reasons, frequently undergo repeat caesareans," she explained.
Beyond the immediate operational environment, medical experts warn of the hidden physical and developmental costs associated with non-medically indicated surgical births. While a C-section can avert disaster in genuine emergencies, unnecessary surgeries expose women to extended recovery periods, post-operative infections, and heightened risks in subsequent pregnancies.

The ramifications extend to newborns as well. A comprehensive 2004 study published in BMC Pediatrics, which examined more than 200,000 Indian births, concluded that infants delivered via C-section faced higher correlations of malnutrition, stunting, and neonatal mortality compared to those born vaginally. Researchers noted a direct link between non-medically indicated surgical births and poorer child health outcomes, alongside a widening gap in nutritional inequality.
Dr. Kala elaborated on the pediatric consequences observed in clinical practice. "We are seeing babies born through surgery having more breathing difficulties immediately after birth, and in the long run, higher risks of obesity, allergies, asthma and weakened immune development," she said, adding that accidental surgical lacerations during the procedure also occur on rare occasions.
Dr. Tandulwadkar acknowledged that patient expectations are also shifting, particularly among urban demographics. "Many women, especially in metropolitan areas, now prefer planned deliveries to avoid prolonged labor or emergency situations. Such preferences must be balanced with sound clinical judgment," she said. She underscored that the ultimate objective must remain evidence-based care. "Every C-section must be based on evidence, with proper counseling and auditing. The goal is safe motherhood, ensuring that every woman receives the right mode of delivery for her specific condition."
Regulatory responses to the phenomenon have historically been limited. In 2018, the Madras High Court ordered the Union Health Ministry to investigate unusually high rates of unnecessary caesareans in Tamil Nadu. While official advisories were subsequently issued to various stakeholders, they lacked enforcement mechanisms, and hospitals remain under no legal obligation to formally justify the clinical indications behind individual surgical interventions.
Public health specialists argue that reversing these trends will require deep structural reforms across the healthcare ecosystem. Dr. Kala advocates for a realignment of institutional priorities. "We must end financial incentives for C-sections and instead reward normal deliveries," she urged. "Educating mothers to trust the natural process, allowing labor to progress and offering midwife-led care can all help. The goal should be safety, not speed or profit."
As India continues to urbanize and the private healthcare sector expands, the prevalence of surgical births remains a central challenge for maternal health policy. For mothers like Khushboo Jaiswal and Shabnam, the overarching hope moving forward is that the fundamental milestone of bringing new life into the world will once again be guided strictly by medical necessity, informed consent, and an active respect for women’s voices when it matters most.